Chamber enlargement in children reflects chronic pressure or volume overload states resulting from intracardiac shunts, valvular stenoses, regurgitation, or cardiomyopathies.
1. Atrial Enlargement Criteria
| Chamber Enlargement | Lead II ECG Criteria | Lead $V_1$ ECG Criteria | Common Etiologies |
|---|---|---|---|
| Right Atrial Enlargement (RAE / P-Pulmonale) | Tall, peaked P wave $> 2.5\text{ mm } (0.25\text{ mV})$ (or $>2.0\text{ mm}$ in neonates). | Positive deflection of P wave $> 1.5\text{ mm}$. | Pulmonary stenosis, Tricuspid atresia, Ebstein anomaly (Himalayan P waves $>5\text{ mm}$), PPHN. |
| Left Atrial Enlargement (LAE / P-Mitrale) | Broad, notched P wave duration $\ge 0.10\text{ s}$ ($\ge 0.08\text{ s}$ in infants) with peak-to-peak notch $>0.04\text{ s}$. | Deep terminal negative component $> 1\text{ mm}$ deep and $> 0.04\text{ s}$ duration (Morris index). | Large VSD, large PDA, Mitral valve stenosis/regurgitation, Dilated Cardiomyopathy. |
| Biatrial Enlargement (BAE) | Tall peaked amplitude ($>2.5\text{ mm}$) AND wide notched duration ($\ge 0.10\text{ s}$) in Lead II. | Biphasic P wave with tall initial positive ($>1.5\text{ mm}$) and deep terminal negative component. | Complex congenital heart disease, Endocardial fibroelastosis, Restrictive Cardiomyopathy. |
2. Right Ventricular Hypertrophy (RVH)
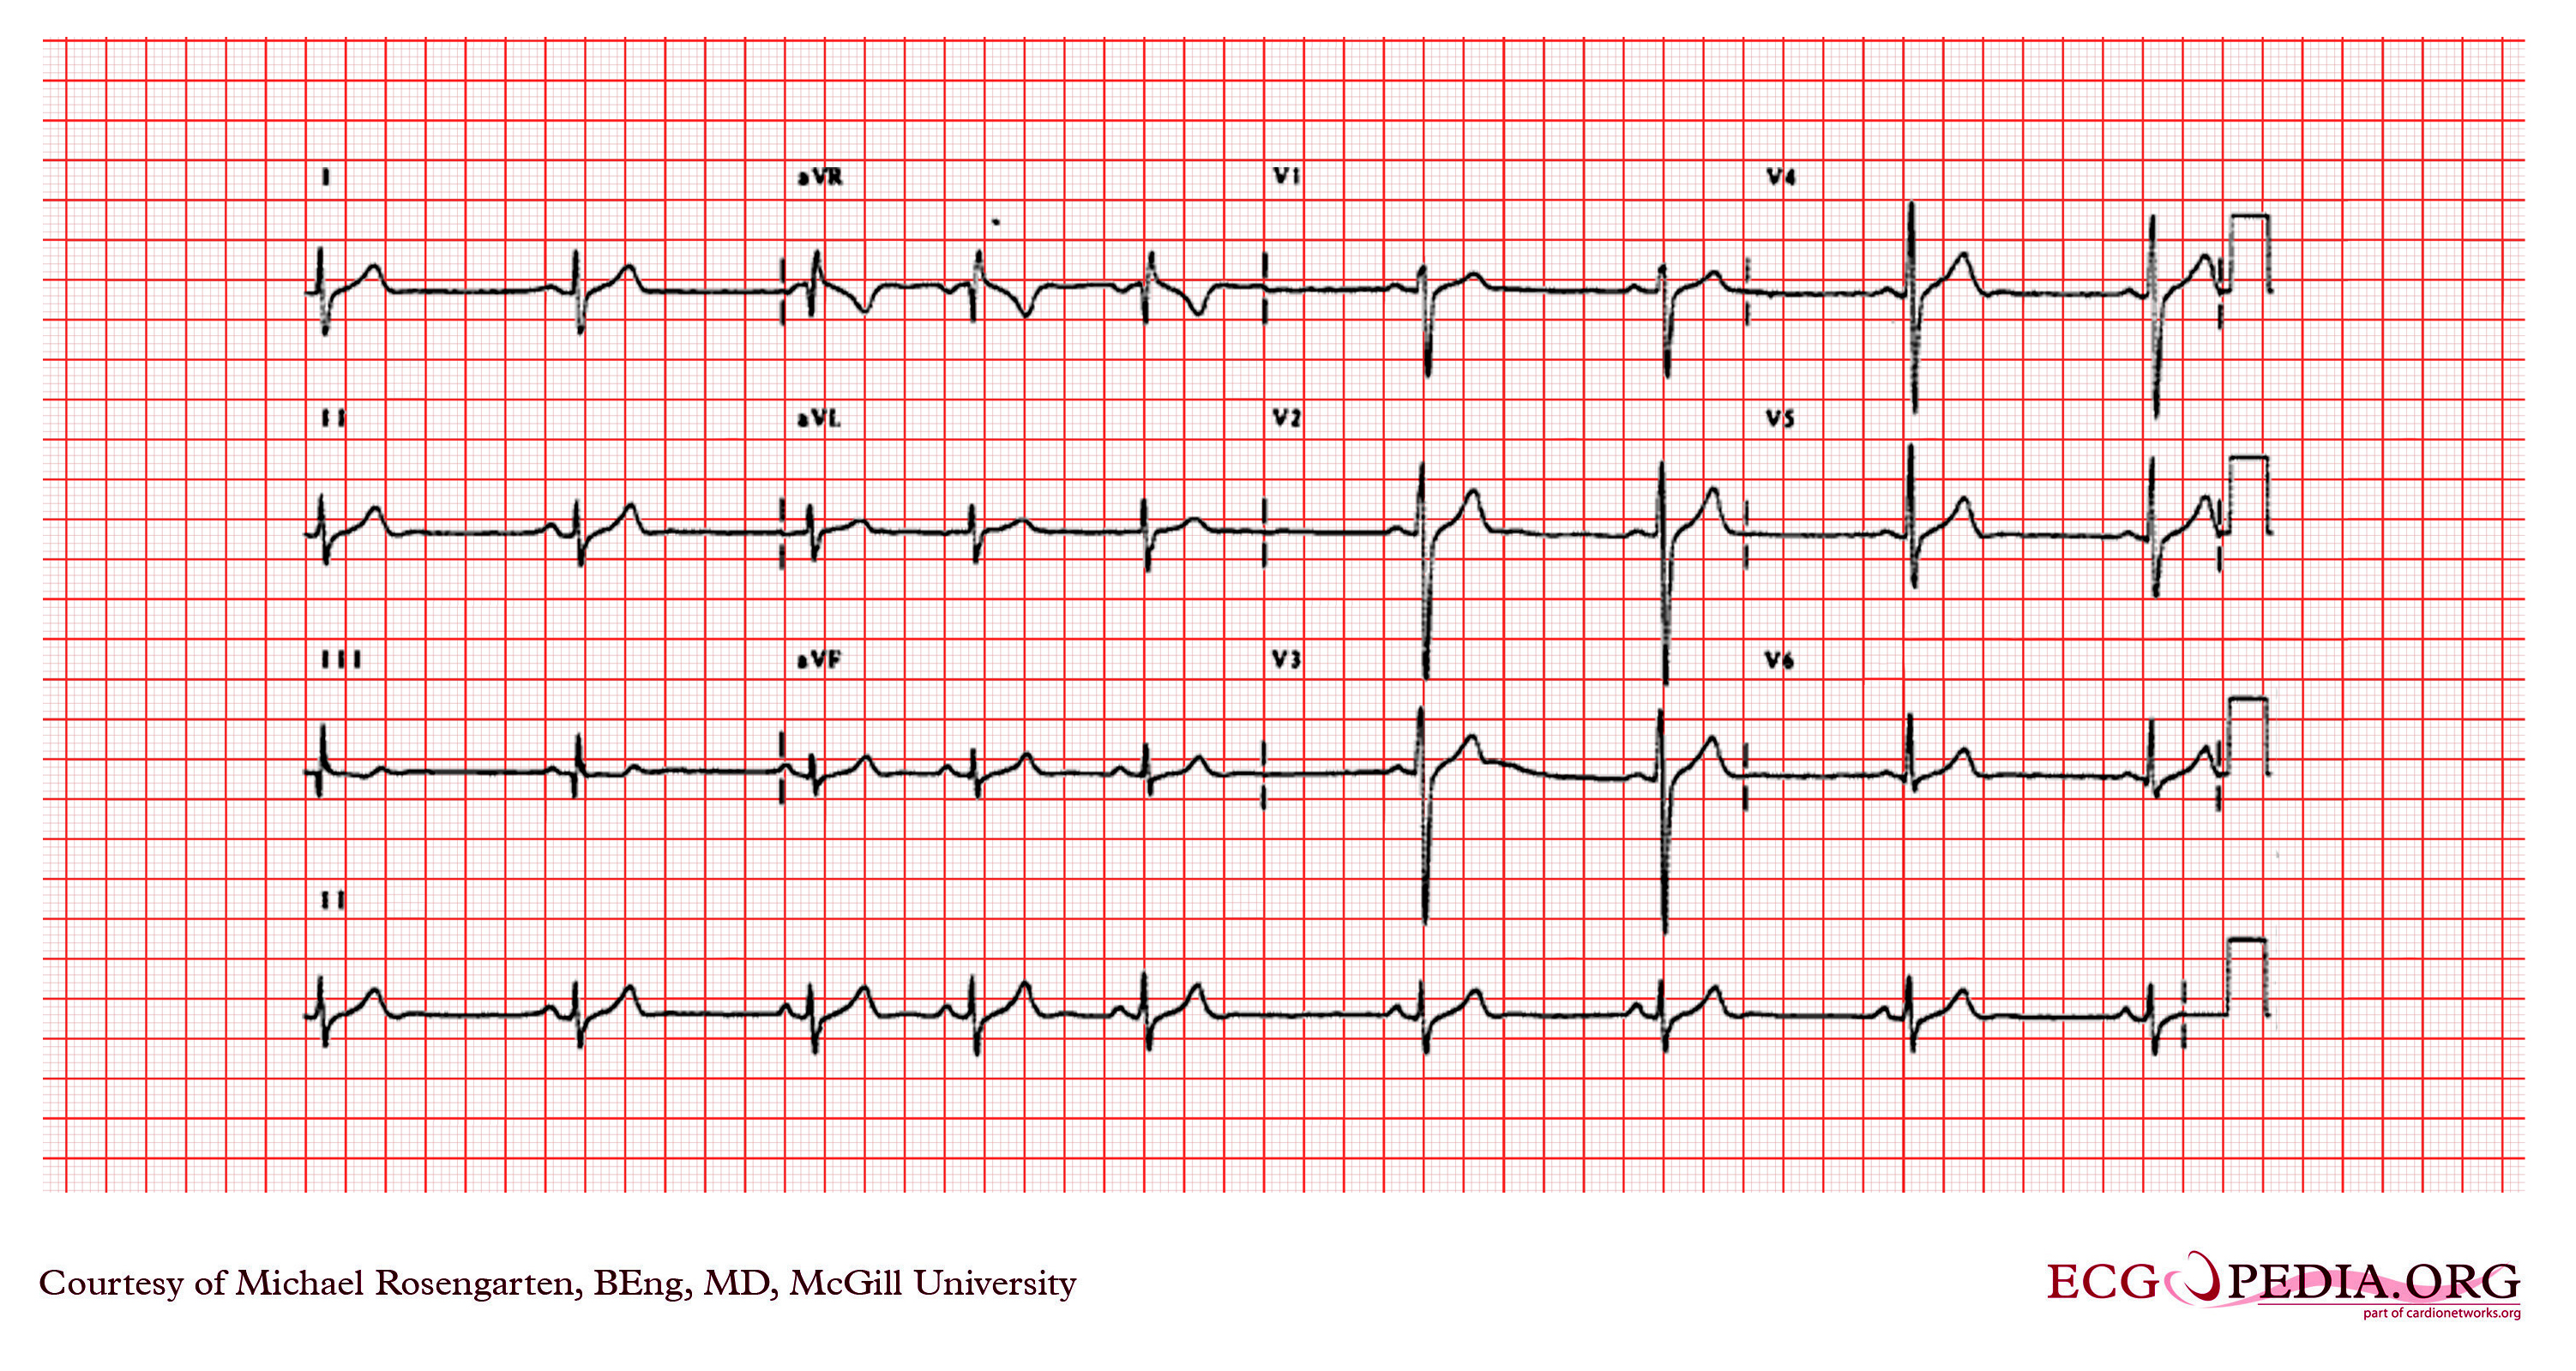 Figure 4.1: Clinical 12-lead ECG of Right Ventricular Hypertrophy in a child showing tall R in V1, deep S in V6, right axis deviation, and upright T wave in V1. Rendered with solid white background.
Diagnostic Criteria for RVH (Park & Davignon):
- $R$ wave in $V_1 > 98\text{th}$ percentile for age.
- $S$ wave in $V_6 > 98\text{th}$ percentile for age.
- $R/S$ ratio in $V_1 > 98\text{th}$ percentile for age.
- $R/S$ ratio in $V_6 < 1.0$ beyond 1 year of age.
- Upright T wave in $V_1$ between 7 days and 8 years of life.
- Presence of $qR$ pattern in $V_1$ (highly specific for severe RV pressure overload).
- RV Strain Pattern: ST segment depression and T-wave inversion in right precordial leads ($V_1 - V_3$).
3. Left Ventricular Hypertrophy (LVH)
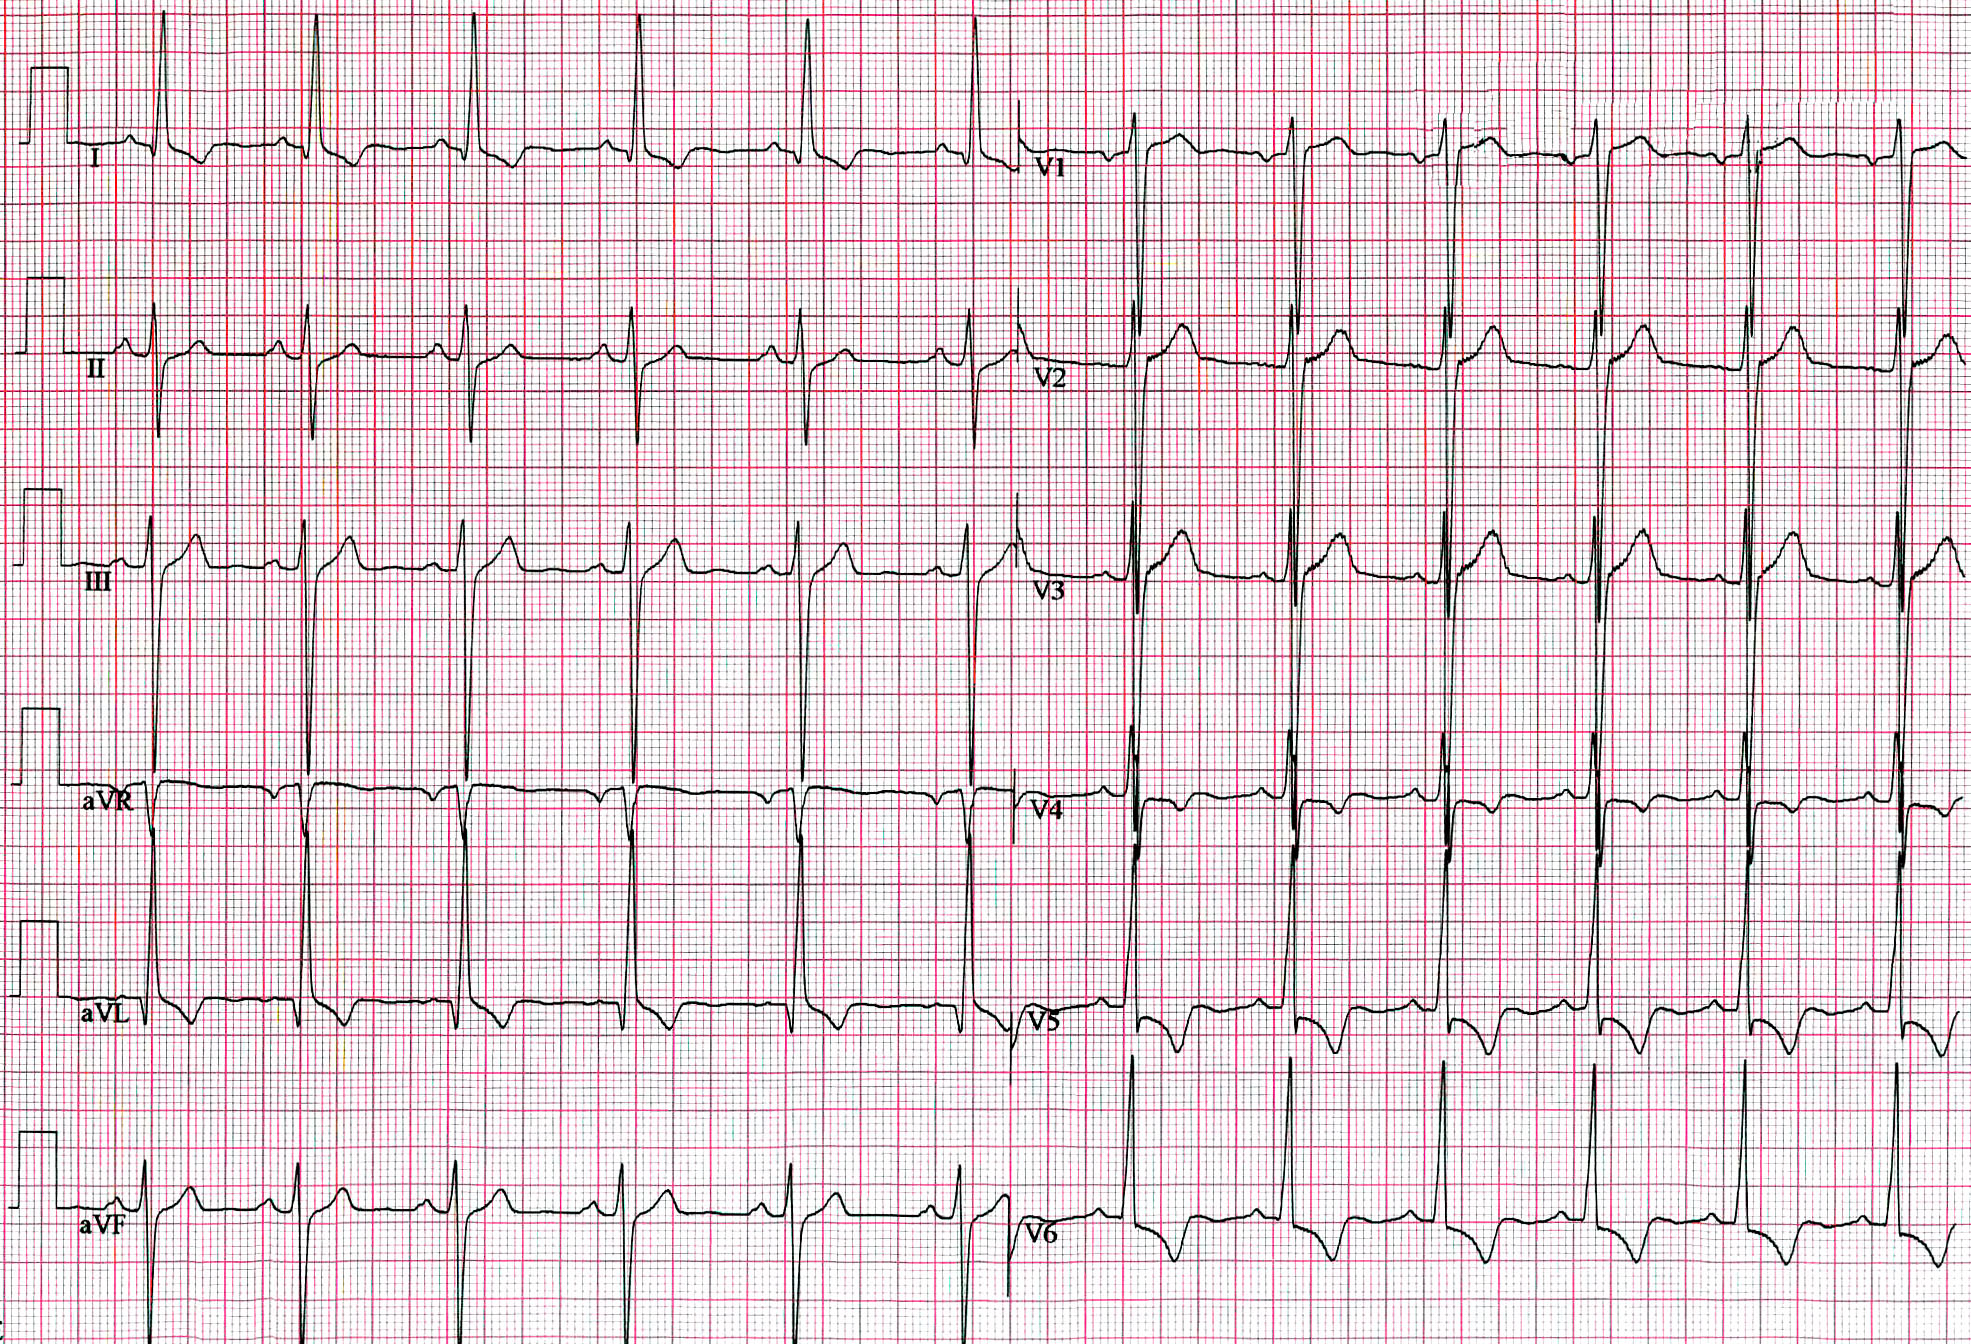 Figure 4.2: 12-lead ECG of Left Ventricular Hypertrophy showing high voltage R waves in V5-V6 and deep S waves in V1-V2. Rendered with solid white background.
Diagnostic Criteria for LVH:
- $R$ wave in $V_6 > 98\text{th}$ percentile for age ($>25\text{ mm}$ in older children).
- $S$ wave in $V_1 > 98\text{th}$ percentile for age ($>20\text{ mm}$).
- Sokolow-Lyon Voltage: $S(V_1) + R(V_6) > 35\text{ mm}$ in adolescents ($>45\text{ mm}$ in young children).
- Abnormal $Q$ wave in $V_5 - V_6$: Depth $\ge 4-5\text{ mm}$ (sign of LV volume overload in VSD/PDA).
- LV Strain Pattern: ST depression $>1\text{ mm}$ with asymmetric T inversion in $V_5, V_6$, I, aVL.
4. Biventricular Hypertrophy (BVH) & The Katz-Wachtel Phenomenon
Important
The Katz-Wachtel Phenomenon:
- Characterized by large, equiphasic, tall biphasic $RS$ complexes in mid-precordial leads ($V_2, V_3, V_4$) where total peak-to-peak amplitude $R + S \ge 50\text{ mm}$.
- Classic Association: Large Ventricular Septal Defect (VSD) or Patent Ductus Arteriosus (PDA) with massive left-to-right shunt.
5. Multimodality Diagnostic Investigations
- Echocardiography: Measures ventricular wall thickness (interventricular septum and posterior wall thickness Z-scores), chamber end-diastolic dimensions, and Doppler estimates of chamber pressures.
- Cardiac MRI (CMR): Gold standard for accurate quantification of RV volumes, ejection fraction, and ventricular mass index.
6. Evidence-Based Clinical Management
- Medical Decongestion: Loop diuretics (Furosemide $1-2\text{ mg/kg/day}$), Spironolactone ($1-2\text{ mg/kg/day}$), and ACE inhibitors (Enalapril $0.1-0.5\text{ mg/kg/day}$) for symptomatic volume overload.
- Surgical / Catheter Intervention: Closure of left-to-right shunts (VSD, PDA) before irreversible pulmonary vascular remodeling develops.