Hypertrophic Cardiomyopathy (HCM) is an autosomal dominant genetic disorder of the cardiac sarcomere characterized by unexplained left ventricular hypertrophy, dynamic outflow tract obstruction, and electrical vulnerability.
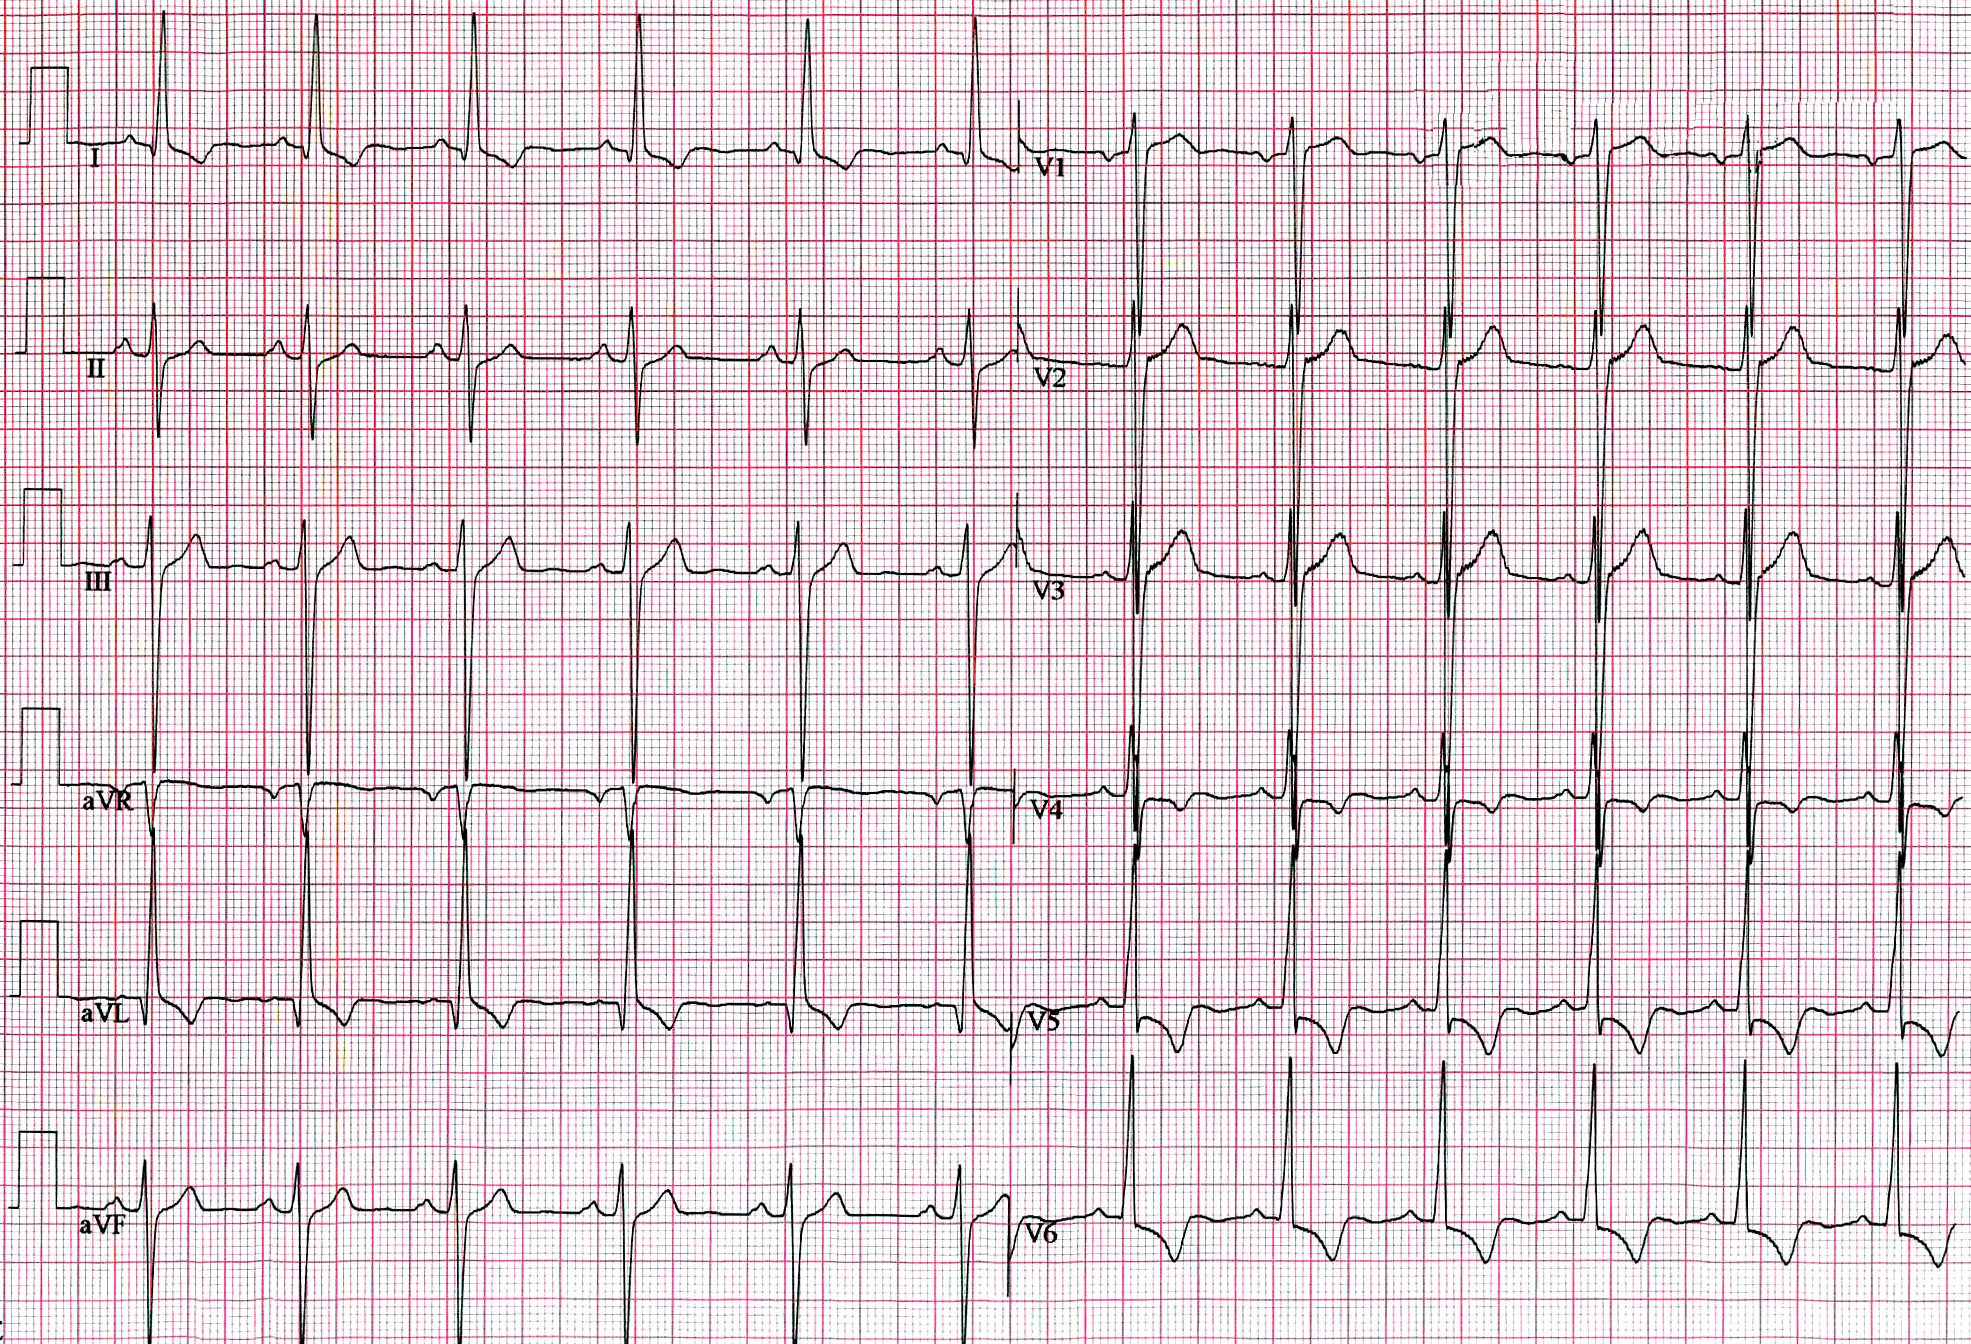 Figure 13.1: 12-lead ECG of Hypertrophic Cardiomyopathy displaying high precordial QRS voltage and deep T-wave inversions across anterior and lateral leads. Rendered with solid white background.
1. Classical Asymmetric Septal Hypertrophy (ASH) vs Apical HCM (Yamaguchi Syndrome)
| Diagnostic Parameter | Classic Asymmetric Septal HCM | Apical HCM (Yamaguchi Syndrome) |
|---|---|---|
| Anatomical Site of Hypertrophy | Basal and mid-interventricular septum ($>15\text{ mm}$, or $>13\text{ mm}$ with positive family history). | Confined to the Left Ventricular Apex ($>15\text{ mm}$). |
| Classical 12-Lead ECG Hallmark | "Dagger-Like" Septal Q Waves: Deep, narrow ($<40\text{ ms}$) Q waves in lateral leads (I, aVL, $V_5-V_6$) and inferior leads; tall R waves; strain pattern. | Giant Negative T Waves ($>10\text{ mm} / 1.0\text{ mV}$) across precordial leads ($V_2 - V_6$); massive precordial QRS voltage. |
| Echocardiographic & Angiographic Finding | Systolic Anterior Motion (SAM) of the anterior mitral leaflet; dynamic LVOT gradient $>30-50\text{ mmHg}$. | "Ace-of-Spades" configuration of the LV cavity during end-diastole on left ventriculography and contrast echocardiography. |
| Hemodynamic Complications | Dynamic LVOT obstruction, secondary mitral regurgitation, exertional syncope. | Apical aneurysm formation, apical thrombus, ventricular arrhythmias. |
2. Multimodality Investigations
- Cardiac Magnetic Resonance (CMR): Identifies patchy, mid-myocardial Late Gadolinium Enhancement (LGE) at the RV insertion points; $\text{LGE} > 15\%$ of LV mass indicates elevated sudden death risk.
- Genetic Testing: Comprehensive sarcomeric multigene panel ($MYH7, MYBPC3, TNNT2, TNNI3$).
3. Evidence-Based Management Protocols
- First-Line Medical Therapy: Non-vasodilating Beta-Blockers (Metoprolol succinate, Atenolol) titrated to resting HR $55-60\text{ bpm}$.
- Novel Cardiac Myosin Inhibitors: Mavacamten ($2.5-15\text{ mg}$ daily) directly inhibits excess actin-myosin cross-bridging, reducing LVOT gradients and eliminating SAM.
- Septal Reduction Therapy: Surgical Septal Myectomy (Morrow Procedure) or Alcohol Septal Ablation (ASA) for severe symptoms refractory to medical therapy with resting/provocable gradient $\ge 50\text{ mmHg}$.
- Sudden Cardiac Death Risk & ICD Implantation: Calculated using the HCM Risk-SCD Score (5-year risk $\ge 6\% \implies$ Class IIa recommendation for primary prevention ICD).